





Arch Pain Treatment in Sydney
Identifying Which Structure Is Causing the Pain
Pain through the arch of the foot is commonly associated with the plantar fascia, but not all arch pain is plantar fasciitis. Pain around the inside of the midfoot, particularly near the navicular bone, can also involve the tibialis posterior tendon. Assessment is used to identify the painful structure and investigate the mechanical loading patterns contributing to the condition.
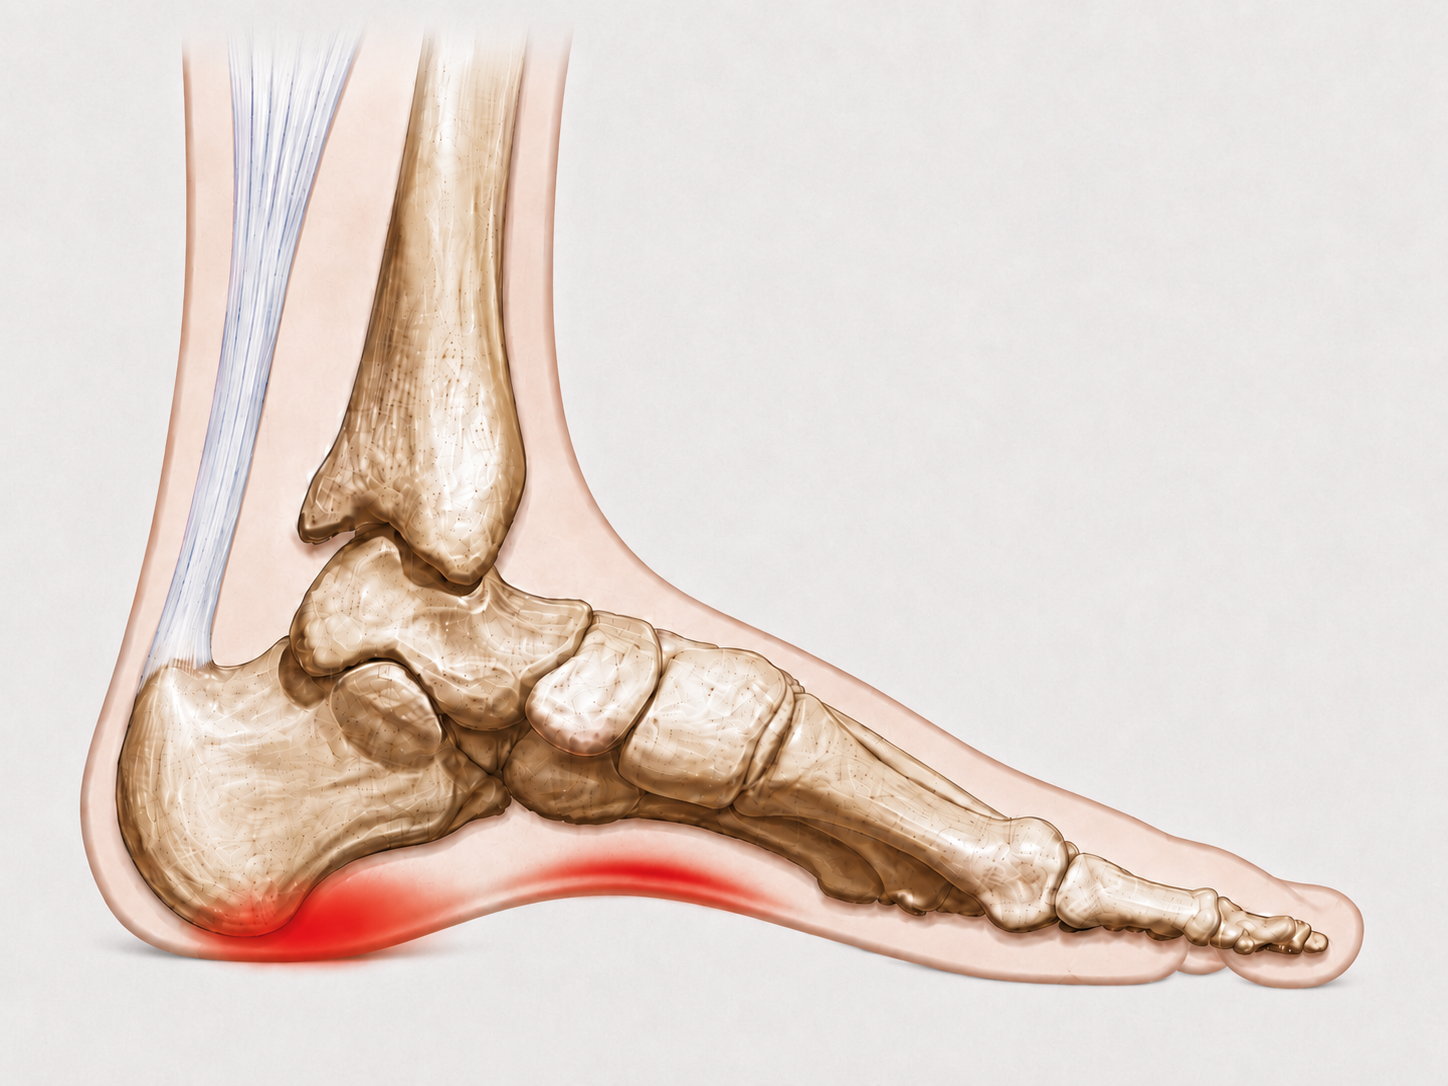
Arch Pain Is a Location, Not a Diagnosis
The arch contains several structures capable of producing pain. Establishing exactly where the symptoms are located and which tissue is painful is an important part of the assessment.
One of the most common causes is plantar fasciitis. Although plantar fasciitis is frequently associated with pain underneath the heel, the plantar fascia extends forward from the heel through the arch. Symptoms can therefore be felt further along the fascia within the medial arch of the foot.
Another important consideration is the tibialis posterior tendon. This tendon passes behind the inside of the ankle and continues towards the navicular region of the midfoot. Irritation around this area can produce pain through the inside of the arch that may initially appear similar to plantar fascia pain.
Two Common Causes of Medial Arch Pain
The precise location of symptoms and the way pain responds to loading can help distinguish between different structures within the arch.
Plantar Fasciitis
The plantar fascia runs from the heel towards the front of the foot. Pain may be concentrated underneath the heel, but it can also extend forward along the medial arch.
Symptoms may be noticeable during the first few steps after rest, when walking barefoot on hard surfaces, or following increased periods of standing, walking or activity.
Tibialis Posterior Tendinopathy
The tibialis posterior tendon travels around the inside of the ankle before attaching predominantly around the navicular region of the midfoot.
Pain associated with this tendon may be felt around the medial mid-arch or navicular region and can increase when the tendon is placed under greater mechanical demand.
Symptoms Associated With Arch Pain
Arch pain can present differently depending on the structure involved and the mechanical environment surrounding the foot.
Medial Arch Pain
Pain may follow the inside of the arch from the heel towards the midfoot, particularly when the plantar fascia is involved.
Navicular Pain
More localised discomfort around the navicular and medial midfoot may indicate involvement of the tibialis posterior tendon or its insertion.
First-Step Pain
Plantar fascia pain can be noticeable during the first few steps after getting out of bed or following a period of rest.
Pain With Walking
Longer periods of walking or standing can increase cumulative loading through the plantar fascia and supporting structures of the arch.
Pain During Activity
Running, gym activity and sport can increase demand through the arch, particularly when combined with changes in footwear or training exposure.
Barefoot Pain
Hard floors and unsupportive footwear can increase symptoms in some presentations by changing the mechanical environment beneath the foot.
Persistent Loading Can Prevent Recovery
Pain can continue when the affected structure remains exposed to repeated mechanical stress. This may occur during walking, standing, exercise or simply through the footwear being used throughout the day.
The important question is therefore not only where the foot hurts, but what continues to load the painful structure.
Understanding What Is Loading the Arch
Several factors can act simultaneously. Assessment considers the mechanical environment surrounding the painful structure rather than examining each factor in isolation.
Footwear
Cushioning, heel height, midsole geometry, forefoot stiffness and overall shoe structure can alter loading through the plantar fascia and medial arch. Different shoes can expose the same foot to very different mechanical conditions.
Calf & Ankle Function
Calf restriction and ankle function can influence the way the body progresses over the foot during walking and running, changing mechanical demand through the arch.
Foot Mechanics
Rearfoot movement, midfoot mobility, arch behaviour and side-to-side asymmetry can influence the forces transferred through the plantar fascia and tibialis posterior tendon.
Activity & Training
Changes in running distance, walking volume, gym activity or sport can increase tissue demand. The cumulative weekly load is often more relevant than a single exercise session.
Standing & Occupation
Long periods on the feet, hard flooring and occupational footwear can create repeated loading through the arch even when there has been no obvious change in exercise.
Tissue Recovery
Symptoms can persist when the painful tissue is repeatedly reloaded before it has had sufficient opportunity to recover. Identifying the continuing source of mechanical irritation is therefore important.
Identifying the Painful Structure
Treatment begins by determining which structure is producing the symptoms. Plantar fascia pain and tibialis posterior tendon pain can occur within a relatively small anatomical region but require different clinical considerations.
Once the painful structure has been identified, biomechanical investigation considers why that structure is being exposed to excessive or persistent load.
Assessment May Include
- Clinical localisation of the arch pain
- Plantar fascia assessment
- Tibialis posterior tendon assessment
- Navicular and medial midfoot assessment
- Calf and ankle function
- Foot posture and arch behaviour
- Walking and functional assessment
- Side-to-side mechanical comparison
- Footwear assessment
- Review of activity and occupational loading
A Clinic Built Around Heel & Foot Pain
Sydney Heel Pain Clinic has treated more than 7,000 patients. Our clinical work includes plantar fascia conditions and mechanical foot pain extending beyond the heel into the arch and midfoot.
Arch pain requires accurate localisation before treatment begins. The objective is to establish which structure is painful, identify the loading patterns surrounding that structure and determine which changes are required to create a better environment for recovery.
Arch Pain Treatment
Treatment is selected according to the structure involved and the mechanical findings identified during assessment.
Footwear Guidance
Footwear is assessed according to the condition and the individual foot. Cushioning, heel height, midsole geometry, stiffness and overall shoe design can all influence loading through the arch.
Calf & Lower-Limb Management
Calf and lower-limb management is selected according to the functional findings. The objective is to address relevant restriction or loading patterns without unnecessarily increasing stress through the painful structure.
Mechanical Modification
Temporary modifications may be used to alter load through the plantar fascia or medial arch while symptoms settle and the mechanical environment is being addressed.
Activity Modification
Running, walking, gym activity and occupational exposure are considered together. Where required, loading can be temporarily modified without automatically removing all activity.
Shockwave Therapy
Shockwave therapy may be considered in selected chronic plantar fascia presentations. Its use depends on the diagnosis, duration of symptoms and the mechanical environment surrounding the painful tissue.
Custom Orthoses
Where foot mechanics are contributing to persistent loading, custom orthoses may be used to modify forces through the painful structure. Devices are modelled using CAD and 3D printed in-house, allowing orthotic geometry and design parameters to be matched to the individual foot.
Arch Pain FAQs
Is arch pain usually plantar fasciitis?
Plantar fasciitis is a common cause of pain through the medial arch because the plantar fascia extends from the heel towards the front of the foot. However, the location of the pain should be assessed rather than assuming that all arch pain involves the plantar fascia.
Can plantar fasciitis cause pain without heel pain?
Yes. Plantar fascia symptoms are not always confined to the heel. Pain can occur further forward along the plantar fascia within the medial arch.
What causes pain near the navicular bone?
Pain around the medial navicular region can involve several structures. One important consideration is the tibialis posterior tendon, which has a major attachment around this region of the midfoot.
Can footwear contribute to arch pain?
Yes. Footwear changes the mechanical environment beneath the foot. Cushioning, heel height, stiffness and shoe geometry can alter demand through both the plantar fascia and the supporting structures of the medial arch.
Are custom orthoses always required?
No. Orthoses are considered when the mechanical findings indicate that modifying foot function may reduce persistent loading through the painful structure. Treatment depends on the individual presentation.
Do I need a GP referral?
No GP referral is required for a private podiatry appointment. Patients attending under an eligible Medicare referral plan will require the appropriate GP documentation.
Clinical Appointments for Arch Pain
Appointments are available at Sydney CBD, Miranda, Crows Nest and Parramatta. Bring several pairs of frequently worn shoes to the appointment where possible.